A flagged low white cell count reads, to almost everyone who sees one, as a statement that their immune system is failing. That is the fear the search is really about, and it deserves a direct answer before anything else.
A low total white cell count is common, and most of the causes on the authoritative lists are not immune failure. It is a finding to have explained rather than a verdict, and the explanation frequently turns out to be ordinary.
The opposite direction, a raised count, is covered by this cluster's pillar, what a high white blood cell count means, which makes the same argument in the other direction.
What the number is and what MedlinePlus publishes
MedlinePlus, in its Medical Encyclopedia entry "WBC count" (review/update date 3 February 2025, updated by Warren Brenner, MD), gives the reference figure: "The normal number of WBCs in the blood is 4,500 to 11,000 WBCs per microliter (4.5 to 11.0 × 10⁹/L)."
It adds the caveat that appears on every MedlinePlus laboratory page and is more important than it looks: "Normal value ranges may vary slightly among different labs. Some labs use different measurements or may test different specimens. Talk to your provider about your test results."
On the low direction it states: "A low number of WBCs is called leukopenia. A count less than 4,500 cells per microliter (4.5 × 10⁹/L) is below normal."
The lab-variation note matters unusually much for this test, because the intervals differ enough between laboratories that a value flagged low on one report would sit inside the interval on another. Why your lab's reference range is different explains where those intervals come from and why both can be correct.
What MedlinePlus lists as causes
The same page names bone marrow problems, cancer medications, autoimmune disorders, liver or spleen disease, radiation therapy, viral infections, severe bacterial infections and stress.
Two entries on that list are worth pulling out because they account for a great many results.
Viral infections. A white cell count taken during or shortly after a viral illness can be low for that reason, and it recovers. This is one of the most common explanations there is, and it is invisible on the report because the report does not know you were unwell last week.
Severe bacterial infections. This one is counterintuitive, because bacterial infection is the classic cause of a raised count. MedlinePlus's "Blood differential test" page (review/update 3 February 2025) also lists severe bacterial infection among the causes of decreased neutrophils. A demand large enough can outstrip the supply, and the count falls rather than rises. It is worth knowing that the simple rule has an exception, because the exception is the more serious situation.
Medicines appear on the list through cancer medications, and other medicines can be relevant too. This page does not advise anyone to stop or change a medicine, and nobody should do so on the basis of a blood result and a web page. It is a question to raise with the prescriber, who has the whole picture.
The line that matters more than the total
The total count is the sum of several cell types, and they do not all carry the same weight for this particular worry.
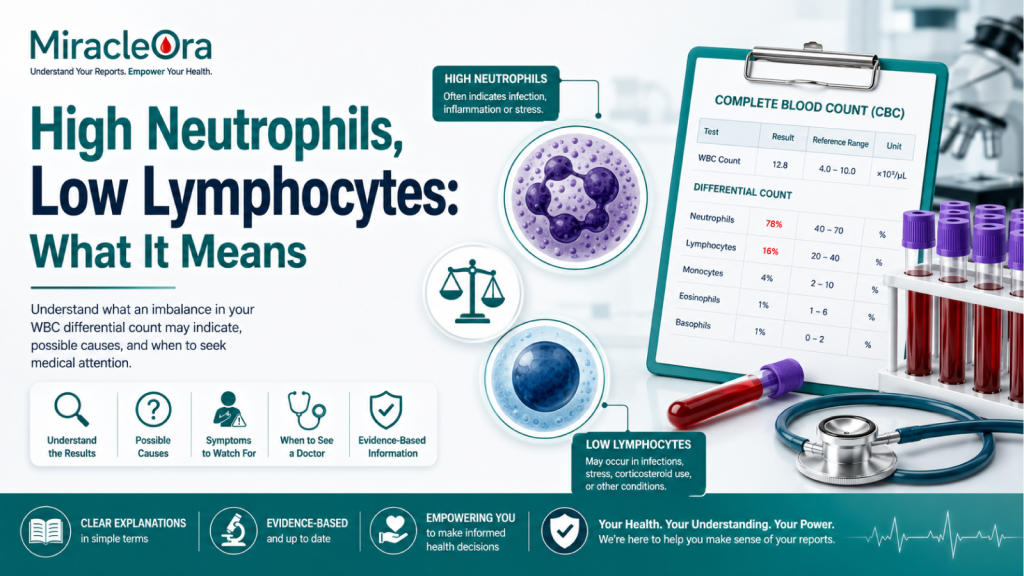
Neutrophils are the largest share in most adults and are the cells most involved in the everyday defence against bacterial infection. So a total that is low mostly because neutrophils are low is a different situation from a total that is low mostly because lymphocytes are low, even when the totals are identical.
This is why a clinician looking at a low white cell count will look at the differential, and specifically at the absolute neutrophil count rather than the percentage. A percentage is a share of a total, so it moves when the total moves, without the cell type itself having changed. The difference between a CBC and a CBC with differential covers what the breakdown adds and whether your report has one.
How low is significant is not a question this page answers. That determination depends on the person, their history, their medicines and what is causing it, and it is made by the clinician who ordered the test. A number published as a line to cross gets read by the person sitting just above it as permission to wait, and that reader is the one it would harm.
Feeling completely fine
This is a common combination and it is not a contradiction.
Reference intervals are constructed so that a proportion of entirely healthy people fall outside them. A result just below an interval is a statistical event before it is a medical one, and an abnormal blood test when you feel fine works through the arithmetic behind that.
There is also natural variation between individuals. Some people run consistently lower than the population interval and are perfectly well, which is one of several reasons a clinician values a series of results over a single one.
None of that means a low count should be dismissed. It means the useful next step is usually a repeat and a look at the differential, not alarm.
Why a repeat is the normal next step
A single count is a snapshot of a system that changes through the day and in response to illness, stress and medicines.
A repeat a few weeks later answers a question the first result cannot: is this where this person sits, or is it moving? A stable mild reduction and a falling count are different findings, and only the second reading distinguishes them.
If you are asked to come back for another test, that is the ordinary procedure rather than a sign that something concerning was found.
What the count cannot tell you
It cannot tell you whether you have an infection. Can a CBC detect infection covers that in full: the count responds to many things and its response is not specific.
It cannot tell you that your immune system is failing. That is a clinical assessment involving how often you actually get ill, what kinds of infections, how they behave, and what else is going on.
And it cannot be interpreted from the flagged line alone. The rest of the report is part of the answer, and how to read a CBC report covers finding your way around it.
What to bring to the appointment
- The whole report, not the flagged line.
- Any recent illness or vaccination, with dates. Viral infection is on MedlinePlus's own list.
- Every medicine you take, including ones you would not think of as medicines.
- Previous results, if you have any. A trend is worth more than a value.
- How you actually are. How often you get ill and how those illnesses behave is information the report does not contain.
The short version
- MedlinePlus (3 February 2025) puts the normal range at 4,500 to 11,000 per microliter and defines leukopenia as below 4,500, with ranges varying between labs.
- Its cause list includes viral infections, stress, medicines and severe bacterial infection, alongside the more serious possibilities.
- The neutrophil line matters more than the total for the infection question, and the absolute count matters more than the percentage.
- How low is significant is a clinician's determination, not a published number.
- A low count in a well person is common. A repeat test is the normal next step.
- Never change a medicine on the strength of a blood result and a web page.